All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional. If you are a patient or carer, please visit Know ALL.
The ALL Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the ALL Hub cannot guarantee the accuracy of translated content. The ALL Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The ALL Hub is an independent medical education platform, sponsored by Amgen and Autolus. Funders are allowed no direct influence on our content. The levels of sponsorship listed are reflective of the amount of funding given. View funders.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View ALL content recommended for you
AIEOP-BFM ALL 2017 phase III trial: Blinatumomab vs chemotherapy in pediatric high-risk Ph– B-ALL
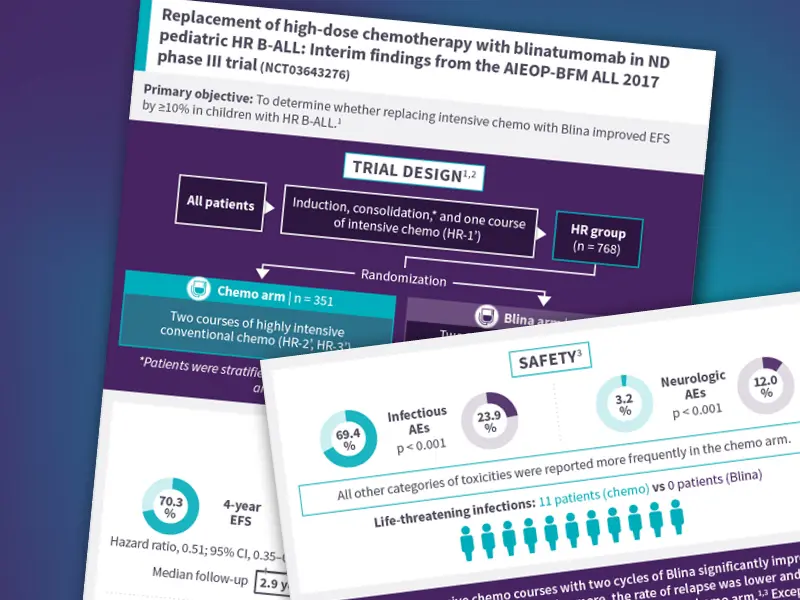
Results from the randomized, international, phase III AIEOP-BFM ALL 2017 trial (NCT03643276), evaluating two cycles of blinatumomab (n = 358) vs two cycles of chemotherapy (control; n = 351) after consolidation in pediatric patients with newly diagnosed (ND) high-risk Philadelphia chromosome-negative (Ph–) B-cell acute lymphoblastic leukemia (B-ALL), were published in The New England Journal of Medicine by Schrappe et al. The primary endpoint was event-free survival (EFS).
Key data: At a median follow-up of 2.9 years, the estimated 4-year EFS was 83.0% (95% confidence interval [CI], 77.4–87.4) in the blinatumomab group vs 70.3% (95% CI, 63.8–75.9) in the control group (p = 0.0002), with an estimated hazard ratio [HR] of 0.51 (95% CI, 0.35–0.73). Treatment-related infections occurred less frequently with blinatumomab vs control (23.9% vs 69.4%; p < 0.001), while treatment related neurotoxic events occurred more frequently with blinatumomab vs control (12.0% vs 3.2%; p < 0.001). Cytokine release syndrome (CRS) Grade ≥2 occurred in 1.1% of patients in the blinatumomab group. Life-threatening adverse events (AEs) were reported in 0.5% of patients receiving blinatumomab vs 4.7% in those receiving control.
Key learning: In this study, two cycles of blinatumomab demonstrated a significantly higher EFS and vs two cycles of chemotherapy in pediatric patients with ND high-risk Ph– B-ALL, supporting the potential of immunotherapy-based strategies as a chemotherapy replacement for first-line treatment in this population
References
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content
This content is accurate as of the date of publication and is not updated retrospectively. Please refer to the latest available evidence, guidelines, and relevant regulatory information when making clinical decisions.