All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional. If you are a patient or carer, please visit Know ALL.
The ALL Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the ALL Hub cannot guarantee the accuracy of translated content. The ALL Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The ALL Hub is an independent medical education platform, sponsored by Amgen and Autolus. Funders are allowed no direct influence on our content. The levels of sponsorship listed are reflective of the amount of funding given. View funders.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View ALL content recommended for you
What are the key considerations when determining the number and duration of blinatumomab treatment cycles?
Featured:
 Sabina Chiaretti
Do you know... Regarding the duration of blinatumomab treatment for B-ALL, which statement best reflects the current evidence?
The ALL Hub was pleased to speak with Sabina Chiaretti, Sapienza University of Rome, Italy. We asked, What are the key considerations when determining the number and duration of blinatumomab treatment cycles?
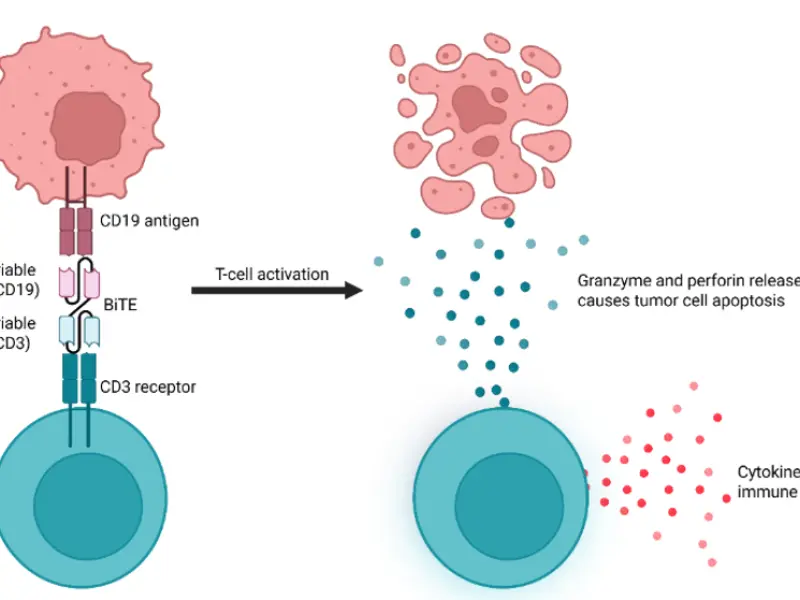
During this interview, Chiaretti discusses considerations when determining the number of blinatumomab cycles to administer in B-cell acute lymphoblastic leukemia (B-ALL), including Philadelphia chromosome (Ph) status, measurable residual disease (MRD), and genomic risk. She also highlights evidence from clinical trials and ongoing studies evaluating different blinatumomab treatment schedules.
How should patients with ALL be selected for blinatumomab treatment?
How should patients with ALL be selected for blinatumomab treatment?
Key points
- The optimal number of blinatumomab cycles needed as part of the treatment of patients with B-ALL remains an area of investigation, with several factors informing the number of cycles administered, including Ph status, MRD response, and genomic features.
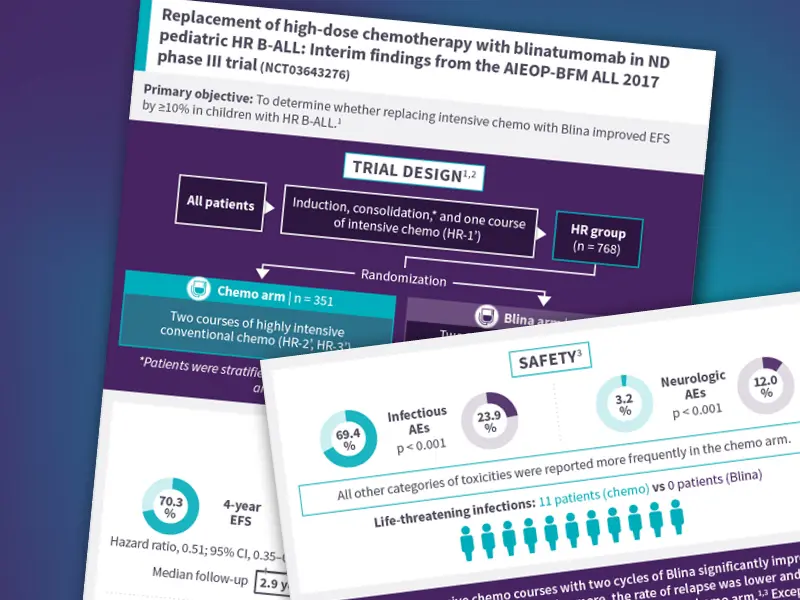
- For patients with newly diagnosed Ph− B-ALL, evidence from the ECOG-ACRIN E1910 phase III trial (NCT02003222) supports the use of 4 cycles of blinatumomab in consolidation.1-3 Further evaluation of blinatumomab in newly diagnosed Ph− B-ALL is ongoing.4,5 The phase III GOLDEN GATE study (NCT04994717) is investigating a treatment strategy incorporating 7 cycles of blinatumomab in older adults with newly diagnosed Ph− B-ALL, which may provide further insight into the use of blinatumomab in this patient population.4,5
- In patients with Ph+ B-ALL, current evidence suggests that additional cycles of blinatumomab may deepen molecular responses.6 For example, in the D-ALBA study, molecular response rates increased with successive cycles of blinatumomab, supporting the use of multiple treatment cycles in this setting.6
- MRD response may help inform treatment duration, and achieving and maintaining MRD negativity is an important consideration when determining the number of blinatumomab cycles. In the E1910 study, in adults with newly diagnosed Ph− B-ALL who achieved MRD-negative remission after initial treatment, the addition of 4 cycles of blinatumomab to consolidation was associated with improved 3-year overall survival (85% vs 68%; p = 0.002) and relapse-free survival (80% vs 64%) compared with chemotherapy alone.3
- Genomic characteristics may also be relevant when considering treatment strategies; advances in genomic and transcriptomic testing have identified molecular subgroups of B-ALL with differing disease characteristics, including Ph-like, MEF2D-rearranged, and KMT2A-rearranged subsets.7
- Overall, the available evidence supports the use of blinatumomab across different ALL settings, while ongoing studies continue to explore optimal treatment schedules and duration.
This educational resource is independently supported by Amgen. All content is developed by SES in collaboration with an expert steering committee. Funders are allowed no influence.
References
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content
This content is accurate as of the date of publication and is not updated retrospectively. Please refer to the latest available evidence, guidelines, and relevant regulatory information when making clinical decisions.